

Cheek and Midface Lift
The standalone cheek lift, or midface lift, was widely performed twenty years ago and is now rarely the right operation. In this practice it is reserved for reconstructive cases. For cosmetic midface ageing, a deep plane facelift combined with fat grafting achieves the same correction more naturally, with less swelling, and without the added risks the older midface techniques carried. This page explains why, and what we recommend instead.
How does the midface age?
The midface is the region between the lower eyelid and the corner of the mouth — the cheek, and the tissue supporting it. Two things happen to it, and for years the first got most of the attention while the second turned out to matter more.
Descent. The soft tissue of the cheek gradually slides downward as the ligaments anchoring it to the cheekbone stretch. The high point of the cheek falls, the groove beneath the lower eyelid lengthens, and the nasolabial fold deepens as tissue piles up above it.
Volume loss. Fat pads in the midface shrink and separate, and the underlying bone itself resorbs. The cheek does not only fall, it deflates.
The distinction matters because the older midface lift operations were designed almost entirely around the first problem. They lifted tissue that had descended. They did nothing about the tissue that was no longer there.
Why we rarely perform a standalone midface lift
The techniques developed in the 1990s and 2000s to lift the midface in isolation — subperiosteal dissection, suspension through the lower eyelid or temple, absorbable fixation devices — have largely been superseded, and for good reasons.
A deep plane facelift with fat grafting accomplishes the same correction, more naturally, with less swelling, and without the added risks. That is the short version, and it is worth unpacking.
- The correction is more natural. The older midface lifts pulled tissue upward in a vertical vector, which is not the direction the tissue actually fell. A deep plane facelift releases the zygomatic retaining ligaments and repositions the cheek along its original axis, which looks like restoration rather than traction.
- There is less swelling. Subperiosteal midface dissection was notorious for prolonged swelling, often taking weeks to settle, and patients frequently found the recovery disproportionate to the change achieved.
- The added risks are avoided. Operating close to the lower eyelid to lift the midface risks pulling the lid downward, producing rounding of the eye or frank lid retraction — a difficult problem to correct and a recognised complication of these approaches.
- It addresses volume, which the midface lift never did. Lifting a deflated cheek produces a lifted deflated cheek. Adding volume is what actually restores midface fullness, and it is why fat grafting has become central rather than optional.
None of this means the older operations never worked. It means the effort-to-result ratio was poor compared with what is available now, and a patient who would once have been offered a midface lift is better served today by a different plan.
What we recommend instead
| Approach | What it does for the midface | Best suited to |
|---|---|---|
| Deep plane facelift | Releases the zygomatic retaining ligaments and repositions the descended cheek along its natural axis, as part of lifting the face as a whole | Genuine tissue descent, jowling, and a fallen midface — the definitive correction |
| Fat grafting | Restores the volume the midface has lost, using your own tissue. Roughly 40 to 50 percent survives permanently | Deflation and hollowing, alone or combined with a lift |
| Voluma or Restylane Lyft | Immediate, non-surgical volume and lift in the cheek, lasting up to 24 months and reversible | Patients wanting a result today, or previewing added volume before committing to surgery |
| Sculptra | Stimulates your own collagen over three to six months for gradual, global midface restoration lasting two years or more | Diffuse volume loss where a gradual change is preferred |
| Thread lifts | Barbed sutures placed to suspend the cheek. A non-surgical option, though the effect is modest and temporary | Rarely our first recommendation — see below |
An important point about non-surgical lifting. Thread lifts are marketed as a non-surgical way to lift the cheek. In practice, restoring volume with fillers or fat grafting produces a lifting effect too — a cheek that is properly supported sits higher and reads as lifted, without sutures placed under the skin, and without the palpability, asymmetry, and short duration that threads can bring. For most patients wanting a non-surgical improvement in the midface, volume is the better route.
When is a standalone midface lift still appropriate?
Reconstructive cases. That is the circumstance in which Dr. Naficy still performs a midface lift as an isolated operation — for example, correcting lower eyelid retraction or midface descent following trauma, prior surgery, or facial nerve injury, where the goal is restoring position and function rather than cosmetic rejuvenation.
For cosmetic midface ageing, it is not the operation we recommend, and we will say so at consultation rather than perform a procedure we do not believe serves you best.
What can be achieved in the midface?
- Restoring the high point of the cheek that has fallen or deflated
- Softening the groove beneath the lower eyelid — the tear trough — by rebuilding the cheek that supports the lid
- Softening the nasolabial fold, more effectively by restoring the cheek above it than by filling the fold itself
- Improving a tired appearance that persists regardless of sleep
- Supporting the lower eyelid, which is measurably improved by midface volume — see the published study below
Published evidence: midface volume and the lower eyelid
Dr. Naficy published a peer-reviewed study on precisely this relationship. In 70 consecutive patients undergoing midface volume augmentation with their own fat, masked investigators measured lower eyelid position before and after surgery. Restoring volume to the upper cheek produced a mean 0.5 mm improvement in margin–reflex distance 2 and a 0.5 mm reduction in scleral show, with the effect still present at a mean follow-up of 316 days.
This is the measured basis for treating the midface with volume rather than traction: rebuilding the platform beneath the lower eyelid supports it, whereas lifting tissue toward the lid can pull it down.
Naficy S, et al. Effect of midface volume augmentation with autologous fat on lower eyelid position. PubMed, PMID 24814272.
Who is a good candidate for midface treatment?
- A flattened or hollow cheek, or loss of the natural cheek highlight
- Shadowing under the eye caused by the cheek falling away beneath the lid
- Deepening nasolabial folds
- A tired appearance that rest does not change
- Good general health, no nicotine use, and realistic expectations
Which treatment suits you depends on whether the dominant problem is descent, volume loss, or both — which is what the consultation establishes.
Who is not a good candidate?
- You want a standalone midface lift because you read about it. We will explain why we no longer recommend it cosmetically, and what we would do instead.
- Your primary concern is jowling or a heavy neck. That needs a facelift or neck lift; midface treatment will not address it.
- Your concern is skin quality — sun damage, texture, fine lines. That is laser resurfacing.
- You use nicotine in any form. Required cessation for at least three weeks before and after any surgical procedure.
- Significant weight loss is planned. Complete it first, since grafted fat shrinks with the rest.
- Uncontrolled hypertension, poorly controlled diabetes, or a bleeding disorder.
What procedures are combined for the midface?
Deep plane facelift with fat grafting: the standard combination. The lift repositions descended tissue; the fat replaces what has been lost. Together they address both mechanisms of midface ageing, which is exactly what the older standalone midface lift could not do.
With lower eyelid surgery or eye bag surgery: the midface and the lower lid are a single aesthetic unit, and treating one without the other frequently disappoints.
With laser resurfacing: volume and position from surgery, surface and texture from the laser.
With brow lift: where the upper face has descended alongside the midface.
What is the recovery?
Recovery depends on which procedure is chosen rather than on the midface itself.
| Approach | Downtime | When the result settles |
|---|---|---|
| Deep plane facelift | Presentable at about 7 to 8 days | Continues refining over several months |
| Fat grafting | Swelling settles over 2 to 4 weeks | Final volume at 3 to 6 months |
| Filler | Swelling and possible bruising for a few days | Assess at two weeks |
| Sculptra | Minimal | Builds over 3 to 6 months |
How much does midface treatment cost?
Because the midface is treated as part of another procedure rather than in isolation, the fee follows that procedure:
- Deep plane facelift — $40,000 to $75,000
- Fat grafting — $6,500 to $15,000 depending on the number of regions treated
- Voluma and other fillers — $750 to $990 per syringe; cheeks typically require two
- Sculptra — $990 per vial, with about one vial per decade of age
Fees are itemized in writing at consultation. Financing is available through PatientFi. Treatment for cosmetic reasons is not covered by insurance.
Fees & payment policies · Non-surgical pricing · Financing
Why choose a facial plastic surgeon for midface treatment?
The midface is where the most consequential judgement in facial rejuvenation gets made: whether the problem is descent, deflation, or both, and therefore whether the answer is lifting, volume, or a combination. Get that wrong and the result is either a lifted deflated face or a filled heavy one.
A practice offering only injectables will recommend injectables. A practice built around one operation will recommend that operation. We perform deep plane facelift, fat grafting, and the full range of injectable volume treatments — so the recommendation follows from what your anatomy needs, and includes telling you when a procedure you have read about is not the right one.
Dr. Naficy performs over 100 facelifts and 100 to 120 fat grafting procedures each year. His practice has been devoted exclusively to facial plastic surgery since 2000. He is certified by the American Board of Facial Plastic and Reconstructive Surgery (ABFPRS), graduated first in his class from the University of Washington School of Medicine, and completed both his residency and fellowship at the University of Michigan. He has been on the clinical faculty of the University of Washington since 1999, has published peer-reviewed research on midface volume and lower eyelid position, and has been recognized in Seattle Magazine's Top Doctors list.
About Dr. Sam Naficy, MD, FACS
What type of anesthesia is used?
It depends on the procedure. Fillers and Sculptra require only topical numbing. Fat grafting is performed under IV sedation or general anesthesia. A deep plane facelift is performed under general anesthesia.
Surgery takes place in our on-site surgery center, which is Medicare-certified and Washington State–accredited. Our anesthesia team has more than 50 years of combined experience, and all providers also hold appointments at the University of Washington or other regional medical centers.
Anesthesia guidelines [21kb PDF]
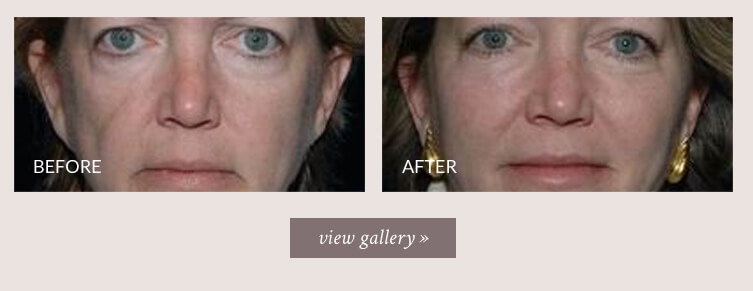
Midface before and after photos
Representative before and after images showing midface correction at Naficy Plastic Surgery. Most patients had more than one procedure; the caption accompanying each photograph describes what was done.
Frequently asked questions about the cheek and midface
Do you perform cheek lifts or midface lifts?
Rarely, and only in reconstructive cases. For cosmetic midface ageing we recommend a deep plane facelift with fat grafting, which achieves the same correction more naturally, with less swelling, and without the added risks of the older midface techniques.
Why did surgeons stop doing midface lifts?
The effort-to-result ratio was poor. They lifted tissue vertically rather than along its natural axis, caused prolonged swelling, risked pulling the lower eyelid down, and did nothing about volume loss — which turned out to be a larger driver of midface ageing than descent alone.
What replaced the midface lift?
A deep plane facelift, which releases the zygomatic retaining ligaments and repositions the cheek properly, combined with fat grafting to restore lost volume. Non-surgically, filler or Sculptra.
What is a SOOF lift or a subperiosteal midface lift?
Older techniques for lifting the midface in isolation, developed in the 1990s and 2000s. They have largely been superseded for the reasons above. We do not perform them cosmetically.
Do thread lifts work for the cheek?
The effect is modest and temporary. Worth knowing that restoring volume with filler or fat grafting also produces a lifting effect — a properly supported cheek sits higher — without sutures under the skin and without the palpability, asymmetry and short duration threads can bring.
Can filler lift my cheeks without surgery?
Yes, to a degree. Voluma or Restylane Lyft placed in the cheek restores projection and produces a genuine lifting effect lasting up to 24 months, and it is reversible. It will not correct significant descent, which needs surgery.
Will treating my cheeks help the hollows under my eyes?
Frequently, yes. Restoring the cheek rebuilds the platform beneath the lower eyelid and reduces the shadow. Dr. Naficy's published study of 70 patients measured a 0.5 mm improvement in lower eyelid position from midface volume augmentation.
Will treating my cheeks soften my nasolabial folds?
Usually more effectively than filling the fold itself. The fold deepens because tissue has descended and accumulated above it, so restoring the cheek addresses the cause rather than the crease.
Is a midface lift the same as a mini facelift?
No. A mini facelift is a limited version of a facelift addressing the lower face and jawline. A midface lift targeted the cheek specifically. Neither is what we recommend for midface ageing today.
How much does midface treatment cost?
It follows the procedure chosen: deep plane facelift $40,000 to $75,000, fat grafting $6,500 to $15,000, fillers $750 to $990 per syringe, Sculptra $990 per vial.
Can the midface be treated without surgery?
Yes — fillers give an immediate, reversible result lasting up to two years, and Sculptra builds gradually over months and lasts longer. Neither corrects significant tissue descent.
I had a midface lift elsewhere and I am unhappy. Can it be corrected?
Frequently. The common problems are lower eyelid retraction or rounding, an unnatural vertical pull, and asymmetry. Assessment establishes what can be improved, and correction often involves restoring volume and supporting the lower lid. See lower eyelid surgery.
Next steps
A midface consultation is principally a diagnostic appointment: establishing whether what is bothering you is descent, volume loss, skin quality, or a combination — because each has a different answer, and the older approach of offering a menu of midface lift techniques answered none of them well.
Naficy Plastic Surgery & Rejuvenation Center is located in Bellevue, Washington, and serves patients from Seattle, the Eastside, and throughout the Pacific Northwest.
Request a consultation · Ask a question · Out of town patients
Medically reviewed by Sam Naficy, MD, FACS, board-certified by the American Board of Facial Plastic and Reconstructive Surgery.




